
Infectious diseases, infection prevention and stewardship
Every hospital acquired infection starts with a decision at the bedside
Eolas puts your infection prevention bundles, antimicrobial guidelines and isolation policies in front of every clinician as cited answers in seconds, and shows your IPC and stewardship teams exactly where guidance is being missed.
- 400,000+
- registered clinicians
- 500+
- hospital and health system sites
- 100% vs 47% prescribing accuracy
- on your own guidance
The problem
Infection metrics are measured on the ward, but the guidance lives in a PDF
Measured, paid and published
The guidance exists but is unreachable
Small teams, whole hospital
What's at stake in your region
The same infection can cost you three times
HAC Reduction Program
Hospitals in the worst performing quartile lose 1% of all Medicare fee for service inpatient payments. Six equally weighted measures: CLABSI, CAUTI, SSI (colon and abdominal hysterectomy), MRSA bacteremia, C. difficile, plus the PSI 90 safety composite.
Hospital Value-Based Purchasing
2% of base payments are withheld and earned back on performance. The Safety domain (25%) holds the same five infections plus the SEP-1 sepsis bundle.
Present on admission non-payment
Medicare, and Medicaid programs, do not pay the higher rate for CAUTI, vascular catheter associated infection and SSI after CABG, bariatric, orthopedic and cardiac device procedures when acquired in hospital.
Reporting and conditions of participation
CDC NHSN reporting through the Inpatient Quality Reporting program (a quarter of the annual update at risk), antimicrobial use and resistance reporting under Promoting Interoperability, and the CMS Conditions of Participation requiring an infection prevention and antibiotic stewardship program.
Coming next
Sepsis readmissions join the Hospital Readmissions Reduction Program, with payment impact from FY2030.
One CLABSI can count against you in the HAC Reduction Program, Value-Based Purchasing and public star ratings at the same time. Preventing it pays back in all three.
Summary of CMS programs as of the FY2027 IPPS final rule. Not legal or reimbursement advice.
Infection by infection
The guidance that prevents it, at the point of care
CLABSI
What prevents it
Insertion and maintenance bundles, line necessity review.
How Eolas helps
Bundle checklists on the phone, daily line review criteria, notifications when the policy changes.
CAUTI
What prevents it
Insertion indications, nurse led removal protocols.
How Eolas helps
Removal criteria answered in seconds for any nurse on any shift.
Surgical site infection
What prevents it
Prophylaxis agent, timing and re-dosing by procedure.
How Eolas helps
Your prophylaxis table searchable between cases.
C. difficile
What prevents it
Antibiotic selection, testing criteria, isolation and cleaning.
How Eolas helps
Stewardship guidance and enteric precautions in one answer.
MRSA and Staph aureus bloodstream infection
What prevents it
Decolonization, screening and line care.
How Eolas helps
Screening and decolonization protocols by unit.
Sepsis
What prevents it
Recognition, SEP-1 bundle timing, empirical antibiotics by source.
How Eolas helps
Your sepsis pathway, SEP-1 bundle elements and empirical choices answered with the source.
MDROs and CPE
What prevents it
Isolation, screening and outbreak communications.
How Eolas helps
Precautions by organism and targeted alerts to every affected team the same day.
Who it is for
Built for the whole infection team
Infectious diseases physicians
Stewardship pharmacists
Infection preventionists and IPC nurses
Quality leaders, CMOs and CNOs
Front line clinicians
The platform
One place for every infection policy
Eolas replaces the search through the intranet for clinical and operational policies. Your teams ask Eolas instead.
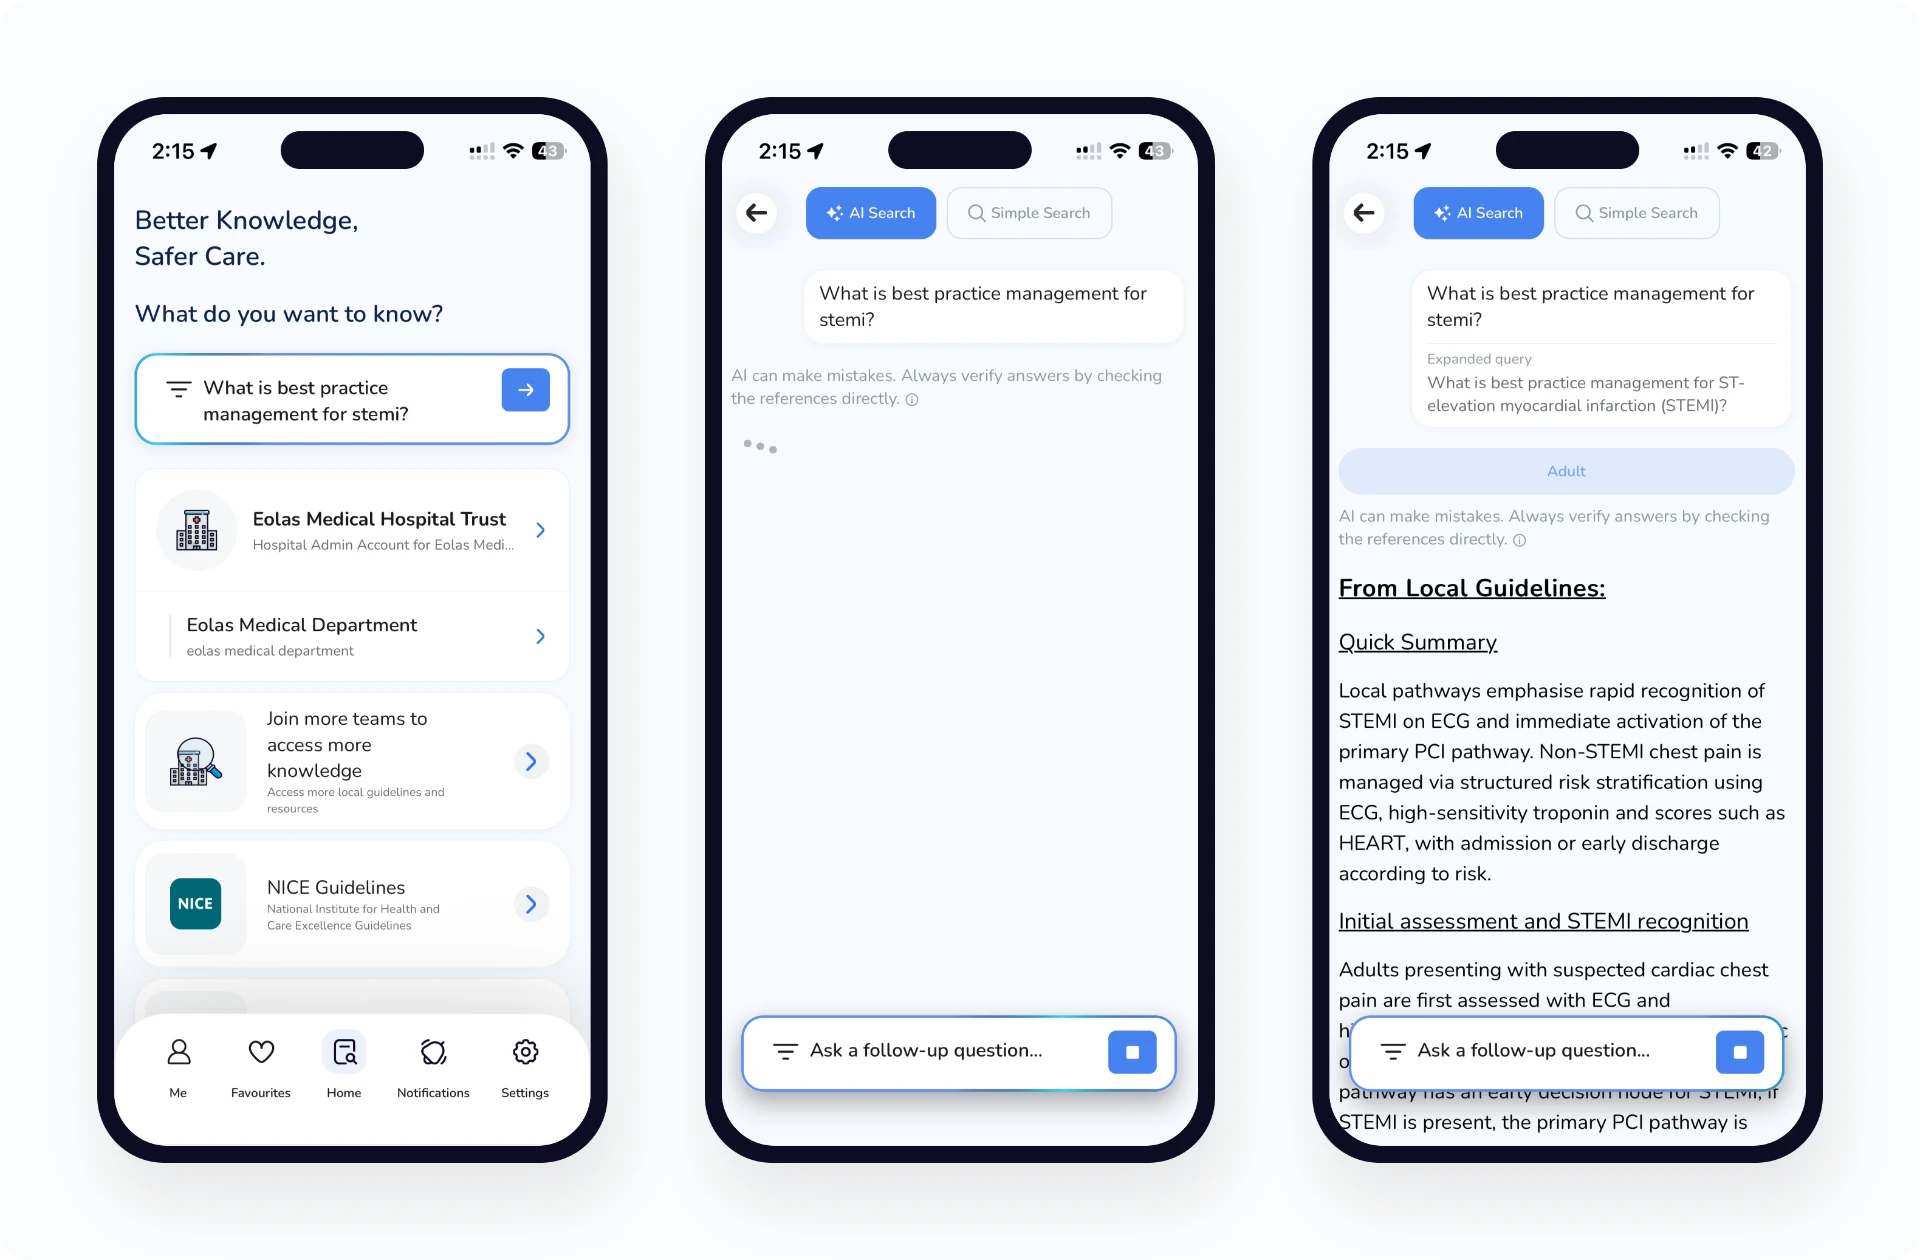
Ask Eolas
Cited answers from your own documents, in seconds.
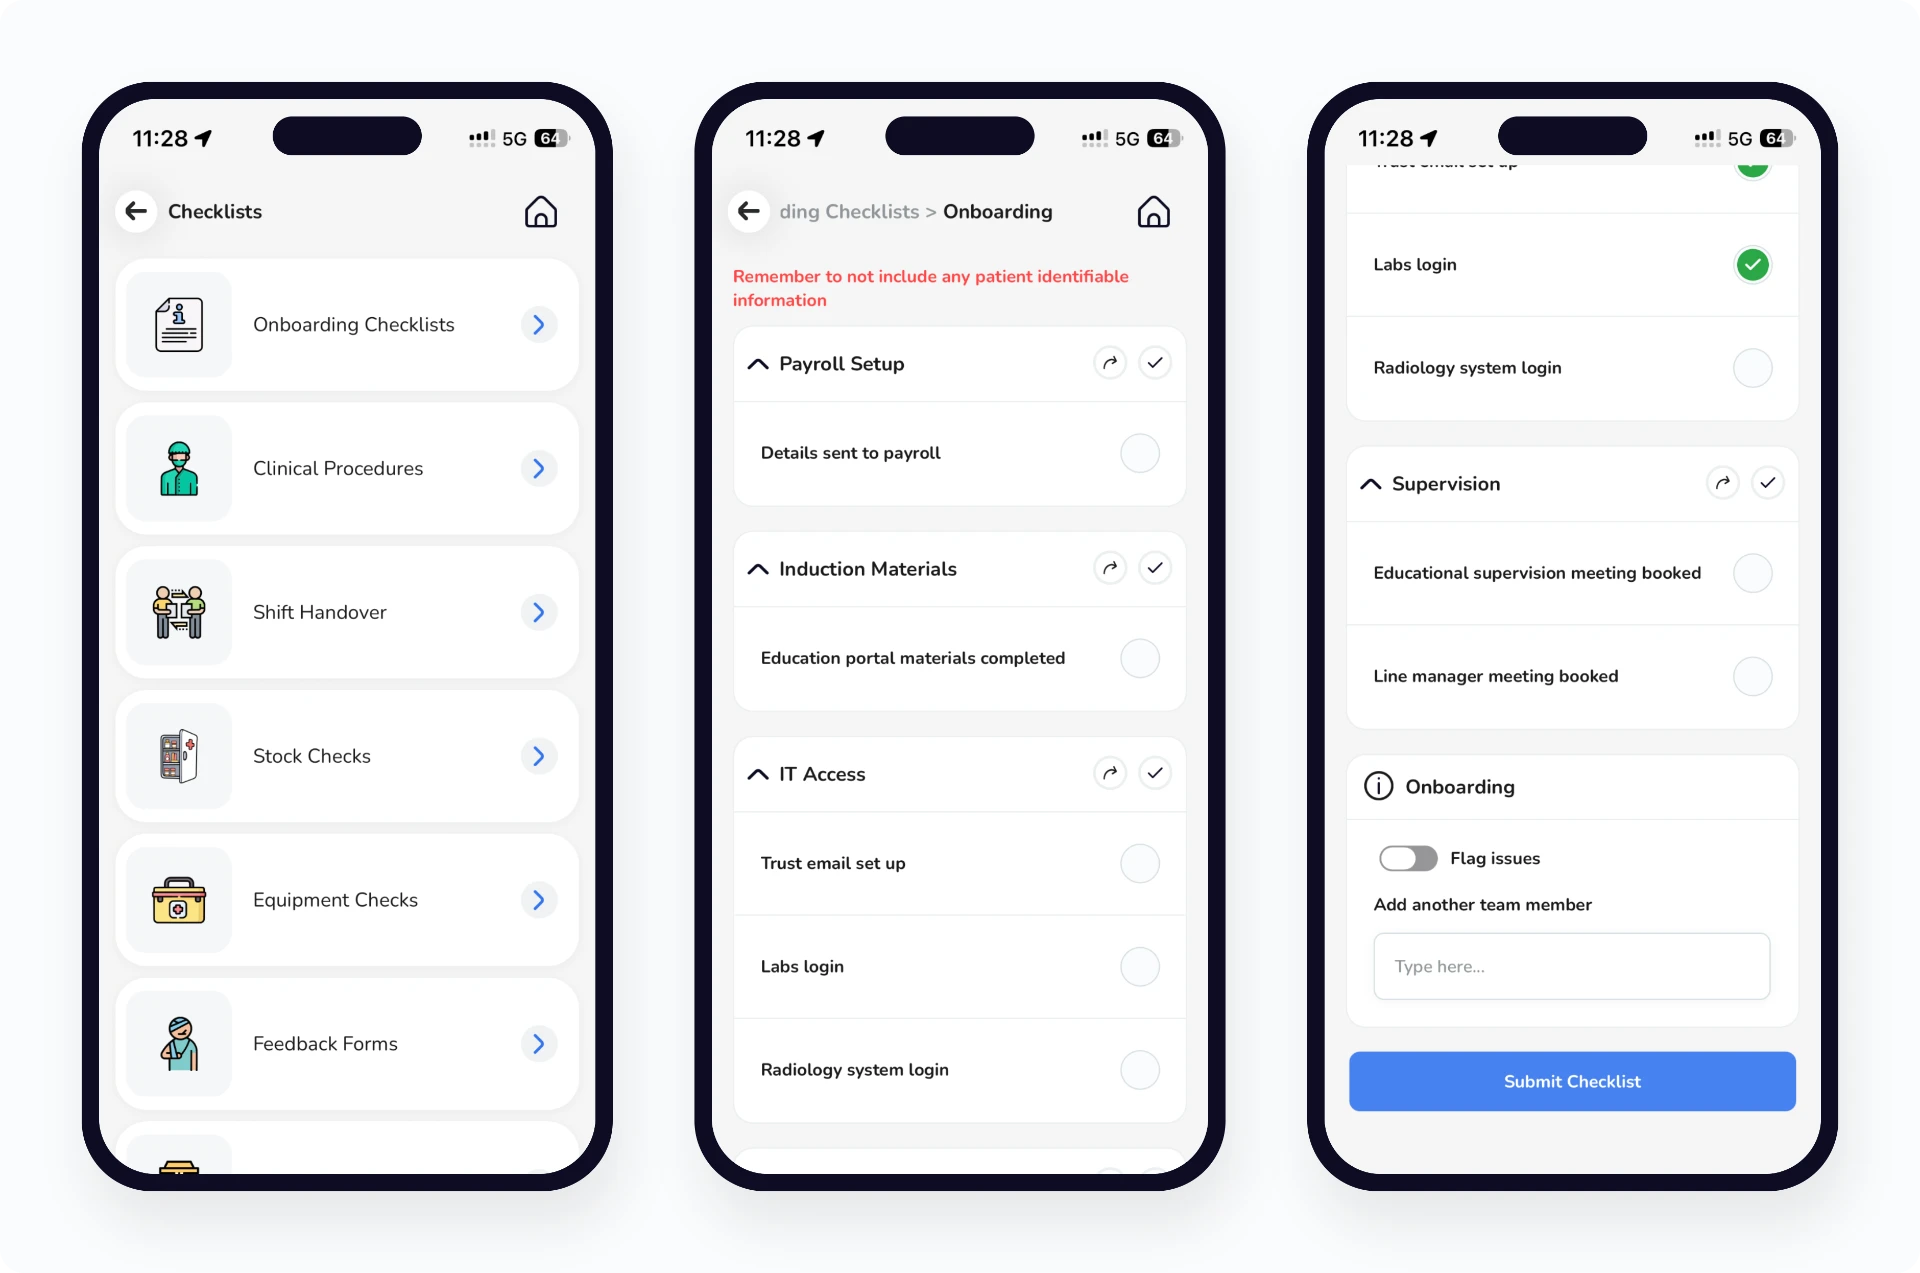
Checklists for bundles
Insertion, maintenance and removal bundles as step by step checklists.
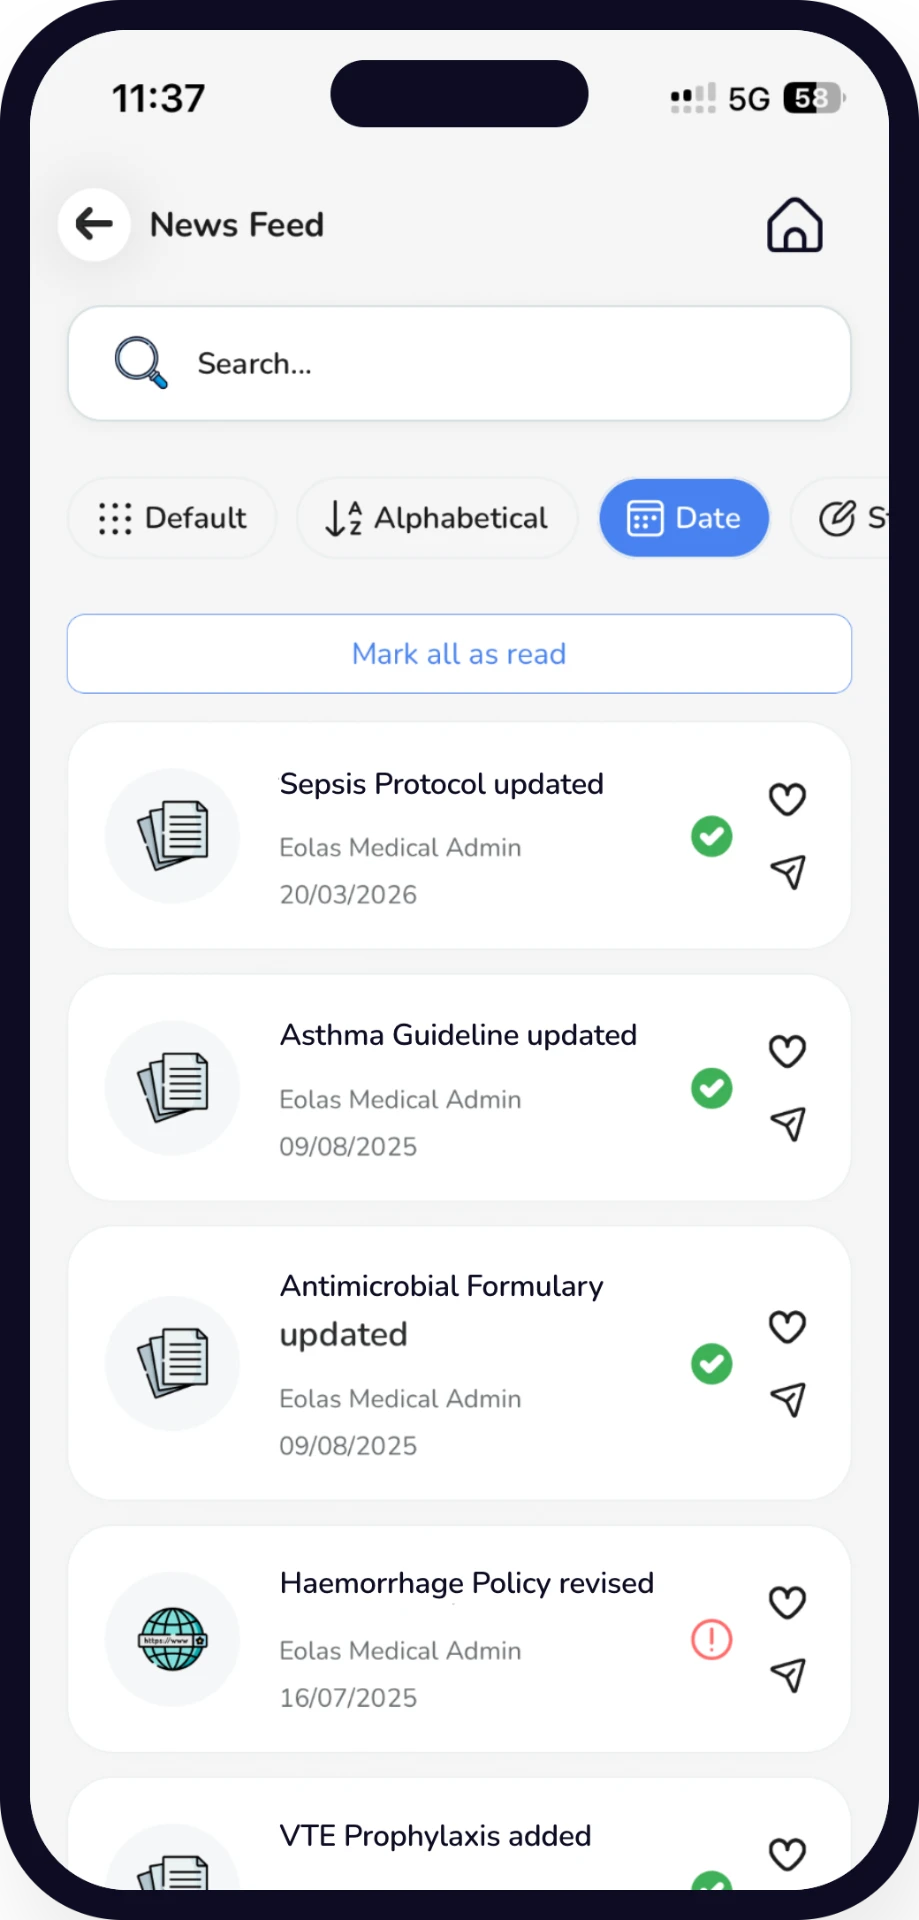
Newsfeed and targeted notifications
Outbreak alerts and policy changes sent to the teams they affect.
Education portal
Bundle training and new hire onboarding in one place.
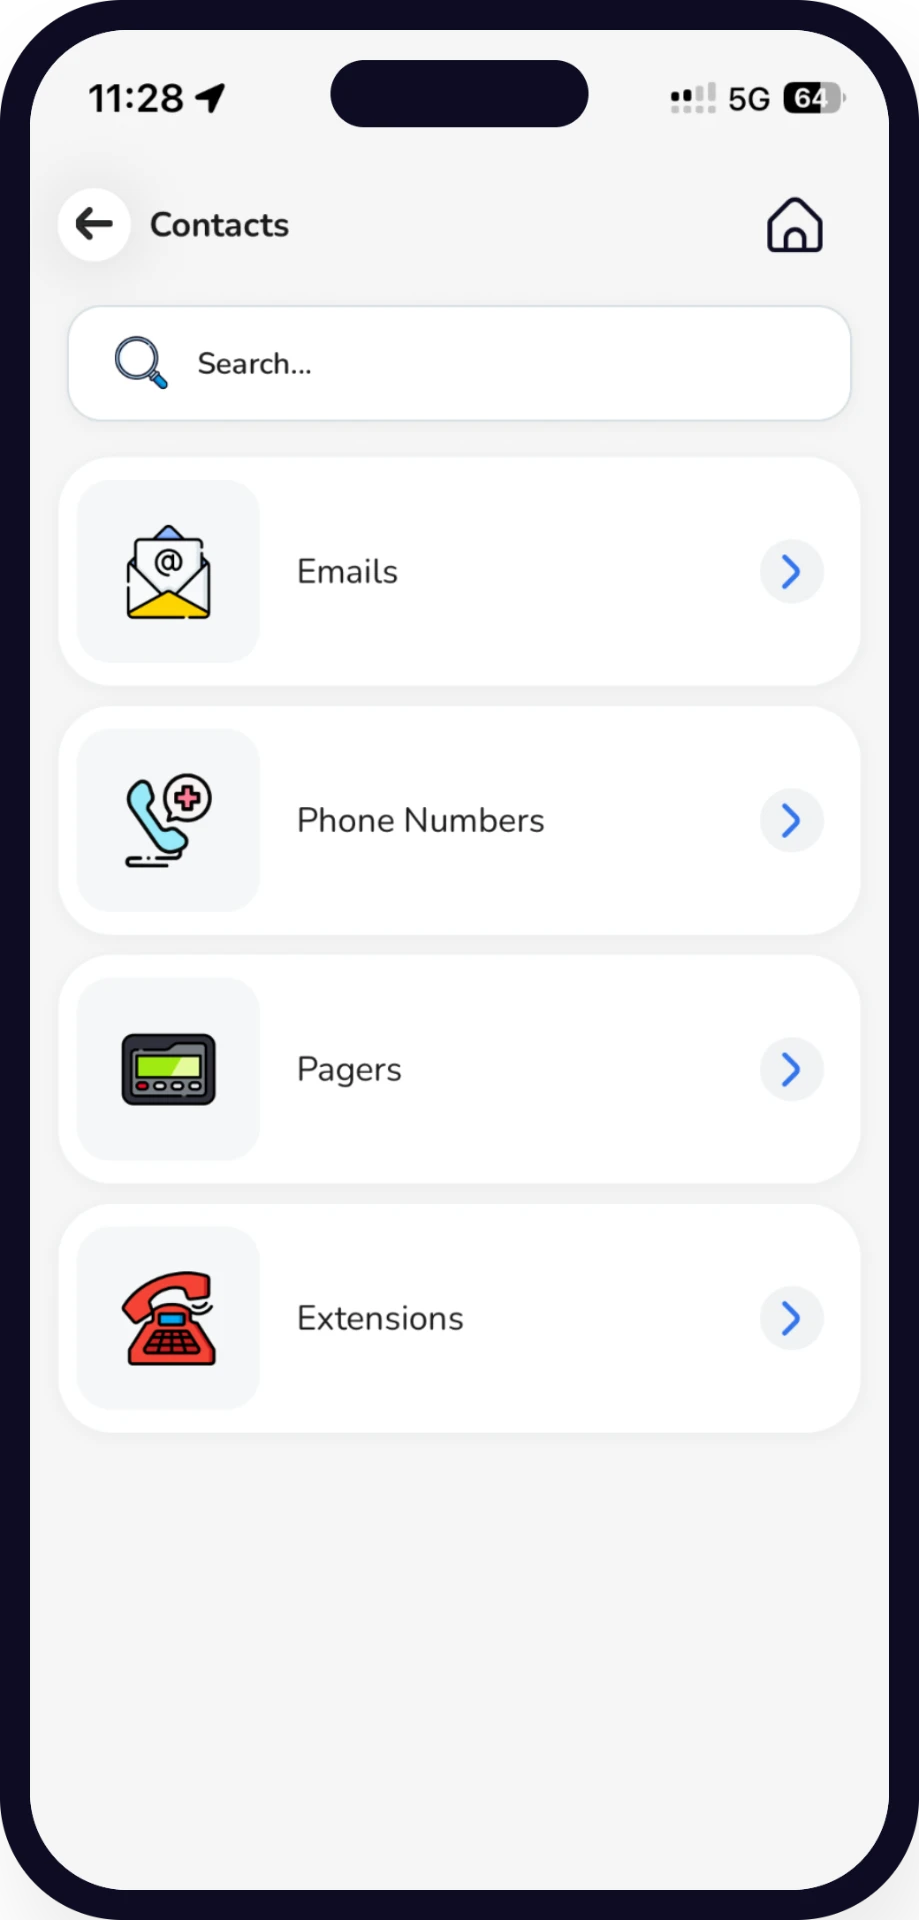
Contacts directory
Who is the on call ID consultant, and how to reach IPC.
Analytics
Searches, gaps and unanswered questions by department.
EHR and point of care integration
Guidance available from the systems clinicians already use.
Where it lands
Three moments in a shift
- At 3am a ward nurse confirms the catheter removal criteria without waiting for the morning round.
- The IPC team publishes new CPE precautions and every affected ward sees them before the next shift.
- The stewardship pharmacist sees the twenty most asked unanswered questions and fixes the guideline that week.
Evidence
In a peer reviewed study by Waldock et al. in npj Antimicrobials and Resistance (2026), clinicians answering with Eolas reached 100% prescribing accuracy against 47% in standard practice.
The number needed to treat was 1.9, meaning fewer than two answers separate standard practice from a correct prescription.
Case study
Carilion Clinic Achieves 4x Increase in Antimicrobial Stewardship Resource Access with Eolas Medical
Within the first month of launch, the team saw sustained engagement and a 4-fold increase in access to stewardship resources compared to the pre-Eolas period.
Evidence partner program
Help us measure the impact on infection outcomes
We have peer reviewed evidence that Eolas changes prescribing. The next question is whether better access to guidance reduces infections such as CAUTI, CLABSI and C. difficile. We are partnering with a small number of hospitals to measure it, with preferential terms for partner sites.
Governance and trust
Owned by your clinicians, governed by your policy team
- SSO and role based access
- Named editors and approvers
- Full version history
- Automatic review dates
- Complete audit trail
- No patient data stored
FAQ
Common questions
How do prescribers see restricted antimicrobial criteria at the point of prescribing?
Eolas surfaces your approval criteria and procedure at the moment of prescribing, rather than in a PDF the prescriber has to go and find. In a peer reviewed study in npj Antimicrobials and Resistance, clinicians using Eolas reached 100% prescribing accuracy against 47% in standard practice.
Can isolation guidance be updated quickly when circumstances change?
Yes. Eolas holds one approved version with named editors and an approval workflow, so isolation guidance can be changed and in clinicians' hands the same day. The previous version becomes immediately unfindable.
Can we upload our own protocols and guidelines, or is the content Eolas's?
The content is yours. Eolas holds your institution's own antimicrobial and isolation guidance guidance, written and approved by your teams, with named editors, an approval workflow, full version history and automatic review dates. Eolas is the system it lives in, not the source of the clinical content.
Does Eolas store patient data?
No. Eolas holds your institution's guidance, not patient records. Access is controlled through SSO and role based permissions, with a complete audit trail of who changed what and when.
Does Eolas reduce hospital acquired infections?
Eolas puts your prevention bundles and stewardship guidance at the point of care and shows where they are not being used. Peer reviewed evidence shows improved prescribing accuracy, and we are measuring infection outcomes with partner sites.
Can Eolas support our infection reporting and inspection readiness?
It does not replace NHSN reporting or your CMS quality submissions. It gives you version history, read receipts and usage analytics that evidence your guidance reached staff, ready for surveys and quality committees.
Does it replace our intranet?
For clinical and operational policies, yes. Teams use Eolas instead of searching the intranet.
The week in clinical evidence, in one email
New studies, guideline updates and journal summaries, pulled together for clinicians who do not have time to go looking.
Bring your infection prevention and stewardship guidance to the point of care
Book a demo and we will show you the same page using your own documents.